PUJ Obstruction
A blockage where the kidney joins the ureter.
What is PUJ Obstruction?
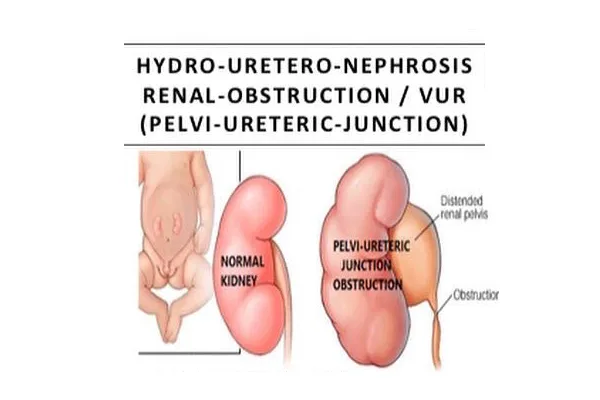
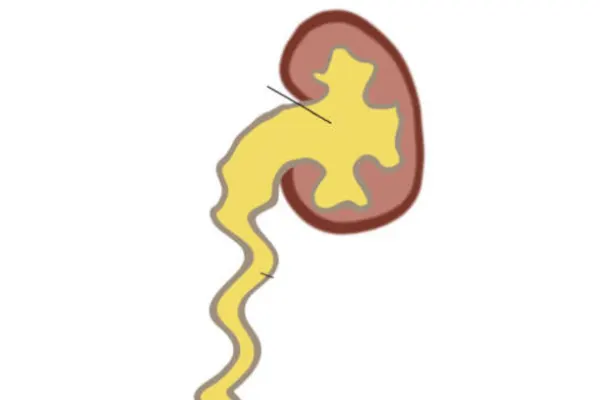
The pelvi-ureteric junction (PUJ) is the point where the funnel of the kidney narrows into the ureter, the tube that carries urine to the bladder. In PUJ obstruction this junction is narrow or kinked, so urine drains slowly and backs up, stretching the kidney.
It is the commonest cause of significant hydronephrosis in children, and is usually present from birth. Some children have a blood vessel crossing the junction that presses on it.
The kidney can tolerate a partial blockage for a long time without symptoms, which is why the swelling is often found on a scan rather than because the child was unwell. The concern is silent, slow loss of function on that side.
In your language
PUJ Obstruction
A blockage where the kidney joins the ureter.
The pelvi-ureteric junction (PUJ) is the point where the funnel of the kidney narrows into the ureter, the tube that carries urine to the bladder. In PUJ obstruction this junction is narrow or kinked, so urine drains slowly and backs up, stretching the kidney.
சிறுநீரக வெளியேற்றக் குழாய் அடைப்பு (PUJ)
சிறுநீரகத்திலிருந்து சிறுநீர் வெளியேறும் இடத்தில் ஏற்படும் அடைப்புதான் PUJ obstruction. இதனால் சிறுநீரகம் வீங்கும். பல குழந்தைகளுக்கு அறிகுறியே இருக்காது — ஸ்கேனில்தான் தெரியும். ரீனோகிராம் பரிசோதனை மூலம் உண்மையான அடைப்பு உள்ளதா, சிறுநீரகத்தின் செயல்திறன் எப்படி உள்ளது என்று அறியலாம். அடைப்பு உறுதியானால் பையலோபிளாஸ்டி எனும் அறுவை சிகிச்சை செய்யப்படும். லேசான நிலைகளில் கண்காணிப்பு மட்டும் போதும். அடிக்கடி வயிற்று வலி, வாந்தி வந்தால் கவனிக்கவும்.
വൃക്ക–മൂത്രനാളി സന്ധിയിലെ തടസ്സം (PUJ)
വൃക്കയിൽ നിന്ന് മൂത്രം പുറത്തേക്കു പോകുന്ന ഭാഗത്തുണ്ടാകുന്ന തടസ്സമാണ് PUJ obstruction. ഇത് വൃക്ക വീർക്കാൻ കാരണമാകും. പല കുട്ടികളിലും ലക്ഷണങ്ങളുണ്ടാകില്ല — സ്കാനിലാണ് കണ്ടെത്തുന്നത്. റീനോഗ്രാം പരിശോധനയിലൂടെ യഥാർത്ഥ തടസ്സവും വൃക്കയുടെ പ്രവർത്തനവും അറിയാം. തടസ്സം സ്ഥിരീകരിച്ചാൽ പൈലോപ്ലാസ്റ്റി എന്ന ശസ്ത്രക്രിയ ചെയ്യും. നിസ്സാര ഘട്ടങ്ങളിൽ നിരീക്ഷണം മാത്രം മതി.
What Parents Notice
Not every child shows every sign. If something on this list matches your child, it is worth an examination rather than a guess.
- Frequently none — found on an antenatal or routine scan
- Episodes of tummy or flank pain, sometimes with vomiting, that come and go
- Pain that appears after drinking a lot of fluid
- A lump felt in the tummy in a baby
- Blood in the urine, sometimes after a minor knock
- Urinary infection with fever
- Poor growth in an infant with both kidneys affected
How It Is Confirmed
- Ultrasound to show the swollen kidney and to check the ureter below is not dilated — which points to the block being at the PUJ
- Diuretic renogram (DTPA or EC scan) — the decisive test, showing the split function of each kidney and whether urine clears after a diuretic
- MCUG in selected children to exclude reflux as the cause of the swelling
- Blood tests for kidney function
- Repeat ultrasound over months — the trend matters as much as any one result
How It Is Treated
- Mild cases with good drainage and good function are watched with repeat scans. Many babies improve without any operation.
- Pyeloplasty is the treatment when obstruction is confirmed: the narrowed segment is removed and the kidney funnel is joined to the ureter widely, so urine drains freely.
- It can be done through a small flank incision or laparoscopically, depending on the child’s age, size and anatomy.
- A stent or drainage tube is often left for a few weeks and removed afterwards.
- Infection or pain episodes are treated as they arise while the decision is being made.
Does My Child Need Surgery?
Not every child with PUJ Obstruction needs an operation. These are the situations in which surgery is advised — and the decision is always made after examining your child, never from a description alone.
The renogram shows obstruction with delayed drainage
The split function of the affected kidney is below normal, or falls on repeat testing
The swelling increases progressively on serial ultrasound
The child has recurrent pain, vomiting or a palpable kidney
There has been an episode of kidney infection with the obstruction
What Happens Over Time
Pyeloplasty relieves the blockage in the great majority of children and further loss of function is generally prevented. Function already lost before surgery may not return, which is the reason for not waiting once obstruction is proven. Long-term kidney health after a successful repair is usually normal.
This describes what usually happens, not what will happen to your child. The surgeon will give you a specific picture after examining them.
Can It Be Prevented?
PUJ obstruction is present from birth and cannot be prevented.
From First Visit to Going Home
What happens, in order, so that nothing on the day comes as a surprise.
Consultation
Dr. Pratheep Samraj examines your child and goes through the history, earlier reports and any treatment already given.
Investigation
Only the tests that change the decision are asked for — commonly an ultrasound, blood tests, and occasionally an X-ray or a scopy.
Explanation
You are told what the condition is, whether it needs surgery, what happens if you wait, and what the operation involves.
Treatment
If surgery is appropriate it is planned with paediatric anaesthetic cover, with ICU and NICU support available in the hospital.
Follow-up
You go home with written instructions and a review date, and you can reach the hospital by phone or WhatsApp in between.
Hospital stay
Typically 3 to 5 days in hospital for a pyeloplasty.
Recovery at home
Discomfort settles within a week or two. School and normal play are usually resumed in 2 to 3 weeks; a stent, if used, is removed in a short procedure a few weeks later.
Follow-up
Ultrasound at intervals and often a repeat renogram at about 3 to 6 months, then longer-term monitoring of the kidney.
Please bring with you: all previous scan reports, blood test reports, discharge summaries, records of any earlier operation, current medicines, and your child’s immunisation card. Photographs on your phone of a swelling that comes and goes are genuinely useful.
Please note: this page is general information about PUJ Obstruction, not advice about your child. Timing, suitability for surgery and the expected result differ from child to child and are decided only after clinical evaluation.
Questions Parents Ask
If your question is not here, send it on WhatsApp — you will get an answer from the hospital team.
Dr. Pratheep Samraj
Consultant Paediatric & Neonatal Surgeon · Palliyadi, Kanyakumari
Super-specialist surgical care for newborns, infants and children, with expertise in paediatric urology, congenital anomalies, gastro-intestinal surgery and minimally invasive surgery.
Related Conditions

A blockage is worth proving before anyone operates.
Many babies improve with no surgery at all, and a renogram is what separates them from the ones who need a pyeloplasty. Bring the scans and you will be told which your child is.
Consultation 10:00 AM - 1:00 PM & 4:00 PM - 8:00 PM · 24-hour laboratory & pharmacy
In an emergency — green vomiting in a baby, a groin swelling that will not go back, severe tummy pain, or a newborn not passing urine or meconium — come straight to the hospital or to your nearest emergency department. Do not wait for a reply to a message.